[White Paper] Decision vs Generative Language Models for Medicare Prior-Authorization Documentation Review
Oct 23, 2026
Janbol Jangabyl
33 min read
This paper is published on Zenodo.
Decision vs Generative Language Models for Medicare Prior-Authorization Documentation Review
AKOS AI, Scottsdale, Arizona, janbol@akos.ai
Technical report, AKOS AI, September 2026. All data in this paper is synthetic; no patient, provider or payer information was used or is described.
Abstract. Prior-authorization review for Medicare outpatient services includes a documentation step in which the clinical packet is checked against a policy checklist and each finding must be supported by a quotation from the record. Generative language models can perform this step well but write their own quotations, which may not match the source. We compare a generative model (Gemini 2.5 Pro inside Palantir Foundry) with a decision model (TypeSafe’s Jev), which answers fixed multiple-choice questions with probabilities, so that a cited sentence is verbatim by design. Both run inside the same routing and evaluation pipeline on 39 synthetic requests with designed outcomes. The engines reach the same documentation headline on 39 of 39 requests and agree on 93% of 256 checklist items. Overall, the decision model’s median latency is about 10 times lower.
1. Introduction
Medicare Administrative Contractors review prior-authorization requests for certain hospital outpatient services [CMS, 2026]. In our implementation the review is a board of seven steps: six clerical and policy checks on structured data, then a documentation step (P7) that asks whether the visit notes and attachments show what the governing policy requires, item by item, with the evidence quoted. P7 is the only step that requires a model to read the clinical record, and the step where an unverifiable answer is most costly.
A decision model such as Jev does not generate text; it selects among options supplied by the caller and returns a probability for each [TypeSafe, 2026]. We ask whether such a model matches a generative model on a fixed-checklist review task, and what the change costs or buys in quotation reliability, latency and confidence reporting.
2. Setup
2.1 Pipeline
Both engines share a two-agent structure: a router chooses which documents to read for each checklist item, an evaluator judges each item against the routed documents, and a final pass reads the whole packet for anything the first pass could not settle. Guards in code enforce the ledger contract for both: a satisfied or contradicted verdict must cite a document and a quotation that appears in it, not applicable is honoured only where the checklist allows it, and an item requiring a signed note is satisfied only by one. Gemini is served inside Palantir Foundry; Jev is an external service reached over an egress connection (Figure 1).
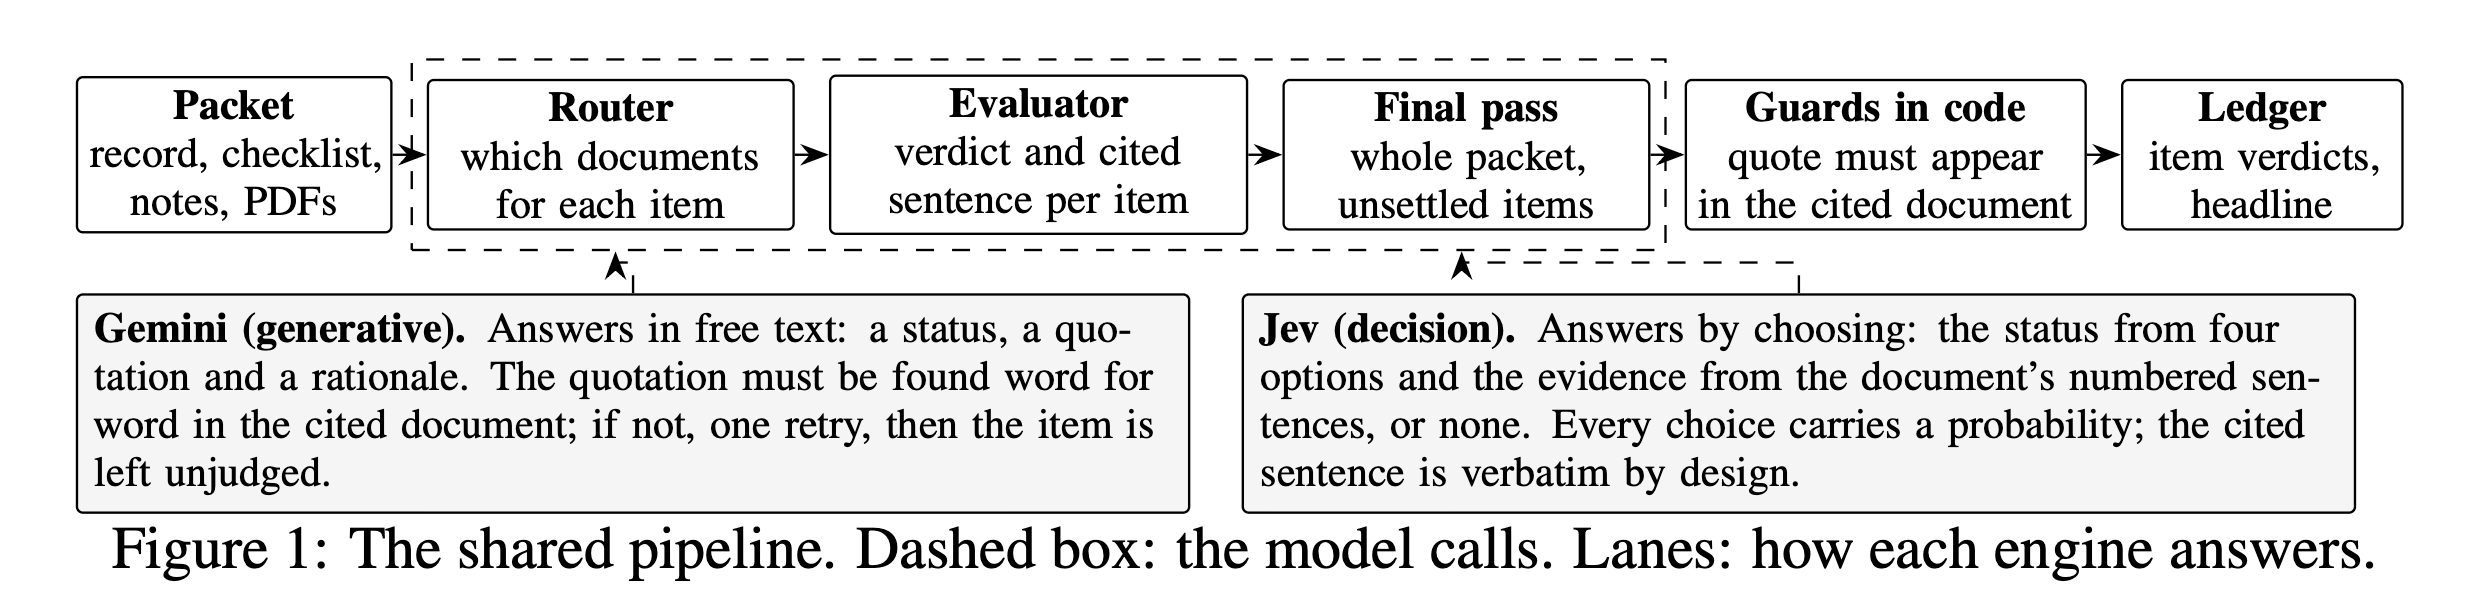
Figure 1. The shared pipeline. Dashed box: the model calls. Lanes: how each engine answers.
2.2 The two engines
Gemini (baseline). The model receives the documents and items and writes back a status, a quotation and a rationale per item. Code verifies that the quotation is a verbatim substring of the cited document; a failed check earns one retry, after which the item is recorded as not evaluated.
Jev. For each item the model answers two multiple-choice questions: which of four statuses (satisfied, not found, contradicted, not applicable) describes the material, and which single sentence, from an enumerated list of all sentences plus none, is the evidence. Because each item’s evidence question enumerates the document, Jev sends about 2.4× Gemini’s input tokens for a comparable number of calls.
2.3 Data
The benchmark is 39 synthetic requests whose outcome turns on the documentation step, each with a synthetic beneficiary, one or two visit notes and, for most, one or two PDF attachments: 18 facet joint interventions, 11 blepharoplasties, 10 vein ablations. 29 were designed to be affirmed and 10 to be non-affirmed on documentation grounds; the failing packets omit or contradict named checklist items. Appendix C shows one request as the engines receive it.
3. Results
Table 1. Outcomes against the designed outcome, 39 requests.
| Gemini | Jev | |
|---|---|---|
| P7 headline matches the plan | 39 | 39 |
| Headline agreement between the engines | 39 of 39 |
Outcomes. Table 1 compares each engine with the designed outcome. Both engines match all 39 expected headlines.
Table 2. Status confusion matrix over the 256 items judged by both engines; rows are Gemini, columns are Jev.
| Gemini \ Jev | satisfied | not found | contradicted | n/a | unjudged |
|---|---|---|---|---|---|
| satisfied | 218 | 6 | 2 | – | – |
| not found | – | 13 | – | – | – |
| contradicted | 1 | – | 8 | – | – |
| n/a | – | – | – | – | – |
| unjudged | 8 | – | – | – | – |
Items. The engines agreed on 239 of 256 items (93%; Table 2). Of the 17 disagreements, eight are Gemini failing to quote one requirement, four are two thin blepharoplasty packets, a single short note each, where Gemini accepted “complains of heavy lids” and “lids appear full” as evidence and Jev did not (the packets were designed to be incomplete), four are on three other packets designed to fail, where Gemini marked satisfied an item Jev marked not found or contradicted, and one is Gemini flagging an additional item on a packet both engines called contradicted. All 17 fall on requests where the headline still agreed; Appendix B lists them and explains why.
Table 3. Jev’s status probability against whether the item was contested: Gemini gave a different substantive verdict, or the packet’s design indicates the verdict is wrong.
| Status probability | Items | Contested |
|---|---|---|
| below 0.70 | 8 | 3 |
| 0.70 to 0.84 | 20 | 1 |
| 0.85 and above | 228 | 5 |
Confidence. Jev returns a probability for the chosen status on every item; Gemini returns none. Low probabilities are rare and the items carrying them are disproportionately the contested ones (Table 3); the counts are too small for a calibration claim.
Table 4. Latency, model calls and tokens: per request, and in total over the 39 requests.
| Per request | Gemini | Jev |
|---|---|---|
| P7 seconds, median | 81 | 8 |
| P7 seconds, 90th percentile / maximum | 147 / 186 | 12 / 139 |
| Model calls, median | 6 | 8 |
| Input / output tokens, median | 6,103 / 1,270 | 14,942 / 2,718 |
| Model calls, total | 249 | 326 |
| Input / output tokens, total | 350,294 / 59,719 | 812,959 / 117,105 |
Latency. See Table 4; Jev’s slowest run (139 s) needed no retry and every other Jev run finished under 20 s.
4. Discussion
Evidence finding. On this benchmark the decision model matched the generative model in outcome, cited a verbatim sentence on every item it judged, reported a probability per item, and did so at a fraction of the latency. This may suggest that selection-based models are the better fit for the evidence-finding portion of documentation review; a model that can only choose among supplied sentences also cannot volunteer text outside them, which simplifies review of what it produces. Reasoning. Gemini’s reading of thin packets was more permissive than a strict checklist intends; requirements that involve computation or cross-sentence reasoning are better placed in code, or in a generative model used deliberately for that purpose.
5. Conclusion
On 39 synthetic prior-authorization requests run through the complete review board, a decision model and a generative model in the same pipeline agreed on the documentation headline 39 times and on 93% of item verdicts. The generative model failed to produce a verbatim quotation on 8 items, all on one requirement; the decision model, which selects rather than writes its evidence, failed on 0, ran with about 10× lower median latency, and reported a probability on every verdict. A decision model is therefore the more suitable component for locating and citing evidence in this setting, with computation and cross-sentence reasoning placed in code.
References
-
Centers for Medicare & Medicaid Services. Prior authorization for certain hospital outpatient department (OPD) services. https://www.cms.gov/research-statistics-data-and-systems/monitoring-programs/medicare-ffs-compliance-programs/prior-authorization-and-pre-claim-review-initiatives/prior-authorization-certain-hospital-outpatient-department-opd-services, accessed September 2026.
-
TypeSafe AI. Jev documentation and pricing. https://docs.typesafe.ai, accessed September 2026.
Appendix A. All requests
Table 5. All 39 requests: the documentation outcome and decision each was built for, each engine’s P7 headline, the decision each engine proposed (A affirmed, N non-affirmed), and P7 seconds, Gemini / Jev.
| Request | Category | Episode | Built as | Designed | Gemini | Jev | Proposed | Seconds |
|---|---|---|---|---|---|---|---|---|
| A01 | Facet joint | initial dx | complete | A | complete | complete | A / A | 121 / 12 |
| A02 | Facet joint | initial dx | complete | A | complete | complete | A / A | 147 / 9 |
| A05 | Facet joint | initial dx | complete | A | complete | complete | A / A | 119 / 7 |
| A06 | Facet joint | second dx | complete | A | complete | complete | A / A | 165 / 7 |
| A09 | Facet joint | initial dx | complete | A | complete | complete | A / A | 144 / 6 |
| A10 | Facet joint | initial dx | complete | A | complete | complete | A / A | 136 / 7 |
| A11 | Facet joint | initial dx | complete | A | complete | complete | A / A | 119 / 6 |
| A13 | Vein ablation | initial dx | complete | A | complete | complete | A / A | 88 / 6 |
| A14 | Vein ablation | initial dx | complete | A | complete | complete | A / A | 68 / 6 |
| A15 | Vein ablation | initial dx | complete | A | complete | complete | A / A | 78 / 8 |
| A16 | Vein ablation | initial dx | complete | A | complete | complete | A / A | 72 / 8 |
| A17 | Blepharoplasty | initial dx | complete | A | complete | complete | A / A | 58 / 6 |
| A18 | Blepharoplasty | initial dx | complete | A | complete | complete | A / A | 61 / 6 |
| A19 | Blepharoplasty | initial dx | complete | A | complete | complete | A / A | 66 / 8 |
| A20 | Blepharoplasty | initial dx | complete | A | complete | complete | A / A | 68 / 6 |
| B01 | Facet joint | initial dx | complete | A | complete | complete | A / A | 155 / 9 |
| B02 | Facet joint | initial dx | complete | A | complete | complete | A / A | 104 / 15 |
| B03 | Facet joint | initial dx | complete | A | complete | complete | A / A | 146 / 12 |
| B04 | Facet joint | initial dx | complete | A | complete | complete | A / A | 140 / 6 |
| B05 | Facet joint | initial dx | complete | A | complete | complete | A / A | 112 / 20 |
| B06 | Facet joint | second dx | complete | A | complete | complete | A / A | 186 / 9 |
| B07 | Facet joint | initial dx | gaps | N | gaps | gaps | N / N | 131 / 11 |
| B08 | Facet joint | initial dx | contradiction | N | contradiction | contradiction | N / N | 121 / 6 |
| B09 | Vein ablation | initial dx | complete | A | complete | complete | A / A | 76 / 10 |
| B10 | Vein ablation | initial dx | complete | A | complete | complete | A / A | 105 / 11 |
| B11 | Vein ablation | initial dx | complete | A | complete | complete | A / A | 72 / 14 |
| B12 | Vein ablation | initial dx | complete | A | complete | complete | A / A | 86 / 8 |
| B13 | Vein ablation | initial dx | gaps | N | gaps | gaps | N / N | 66 / 9 |
| B14 | Vein ablation | initial dx | contradiction | N | contradiction | contradiction | N / N | 71 / 10 |
| B15 | Blepharoplasty | initial dx | complete | A | complete | complete | A / A | 70 / 9 |
| B16 | Blepharoplasty | initial dx | complete | A | complete | complete | A / A | 69 / 12 |
| B17 | Blepharoplasty | initial dx | complete | A | complete | complete | A / A | 67 / 7 |
| B18 | Blepharoplasty | initial dx | complete | A | complete | complete | A / A | 65 / 7 |
| B19 | Blepharoplasty | initial dx | gaps | N | gaps | gaps | N / N | 55 / 4 |
| B20 | Blepharoplasty | initial dx | contradiction | N | contradiction | contradiction | N / N | 80 / 7 |
| N07 | Facet joint | initial dx | complete | N | complete | complete | N / N | 177 / 139 |
| N09 | Facet joint | initial dx | gaps | N | gaps | gaps | N / N | 80 / 5 |
| N10 | Facet joint | initial dx | contradiction | N | contradiction | contradiction | N / N | 81 / 7 |
| N11 | Blepharoplasty | initial dx | gaps | N | gaps | gaps | N / N | 38 / 3 |
Note: N07 is non-affirmed by design although its documentation is complete. The request names no side while its article publishes RT, LT and 50 modifiers, so panel P6 stops it before the documentation step; both engines reproduce that.
Appendix B. Item-level disagreements
Each request is checked against a list of documentation items. For every item an engine answers satisfied, not found or contradicted and must cite the sentence it relied on; when it cannot produce a valid answer the item is left unjudged for a human reviewer. The overall result of a request follows from the item answers: contradiction if any item is contradicted, otherwise gaps if any item is not found, otherwise complete; unjudged items do not change it. Two engines can therefore differ on individual items yet reach the same result, which is what happened on all 17 disagreements in Table 6: in every case the engines agreed on another failing item in the same packet, or differed only on an unjudged item in an otherwise complete packet.
Table 6. The 17 items where the two engines disagreed. For each engine: its verdict, Jev’s probability, and the sentence it cited (or why it gave none). ✓ = the verdict agrees with the label the packet was built with; × = it does not. Unjudged means the engine gave no verdict.
| Request | Built as | Item | Gemini | Jev |
|---|---|---|---|---|
| A06 | complete | Presence of pain for a minimum of 3 months with documented… | unjudged: its quotation did not match the record word for word | ✓ satisfied (1.00): cites “…Documented failure over 11 months: supervised physical therapy 8 weeks (May 9, 2026…” |
| A09 | complete | Presence of pain for a minimum of 3 months with documented… | unjudged: its quotation did not match the record word for word | ✓ satisfied (1.00): cites “…Documented failure over 14 months: supervised physical therapy 12 weeks (April 9,…” |
| A10 | complete | Presence of pain for a minimum of 3 months with documented… | unjudged: its quotation did not match the record word for word | ✓ satisfied (1.00): cites “…Documented failure over 11 months: supervised physical therapy 8 weeks (May 4, 2026…” |
| A11 | complete | Presence of pain for a minimum of 3 months with documented… | unjudged: its quotation did not match the record word for word | ✓ satisfied (1.00): cites “…Documented failure over 11 months: supervised physical therapy 10 weeks (April 19,…” |
| B01 | complete | Presence of pain for a minimum of 3 months with documented… | unjudged: its quotation did not match the record word for word | ✓ satisfied (1.00): cites “…Documented failure over 7 months: supervised physical therapy 8 weeks (May 11, 2026…” |
| B02 | complete | Presence of pain for a minimum of 3 months with documented… | unjudged: its quotation did not match the record word for word | ✓ satisfied (1.00): cites “…Documented failure over 6 months: supervised physical therapy 12 weeks (April 16,…” |
| B04 | complete | Presence of pain for a minimum of 3 months with documented… | unjudged: its quotation did not match the record word for word | ✓ satisfied (1.00): cites “…Documented failure over 11 months: supervised physical therapy 10 weeks (April 12,…” |
| B08 | contradiction | Presence of pain for a minimum of 3 months with documented… | × satisfied: cites “Moderate to severe chronic low back pain, predominantly axial, left paraspinal at…” | ✓ contradicted (0.97): cites “…Moderate to severe chronic low back pain, predominantly axial, left paraspinal at…” |
| B08 | contradiction | For the first diagnostic facet joint procedure, documentation… | ✓ contradicted: cites “Positive straight-leg raise on the left at 40 degrees with pain radiating below the…” | × satisfied (0.61): cites “…I attest that the requirements of the applicable Medicare coverage article for…” |
| B13 | gaps | Doppler ultrasound | × satisfied: cites “Duplex reviewed with the patient.” | ✓ not found (0.56): no sentence in the packet supports it |
| B13 | gaps | Documentation stating the presence or absence of DVT (deep… | × satisfied: cites “Dilated tortuous varicosities of the medial thigh and calf, the right lower…” | ✓ not found (0.95): no sentence in the packet supports it |
| B19 | gaps | Documented excessive upper/ lower lid skin | × satisfied: cites “Lids appear full.” | ✓ not found (0.90): no sentence in the packet supports it |
| B20 | contradiction | Visual field studies/exams | × satisfied: cites “ANALYZER - 30-2 SUPERIOR FIELD, TAPED VS UNTAPED Patient: Theodore Marchetti Exam…” | ✓ contradicted (0.74): cites “HUMPHREY VISUAL FIELD ANALYZER - 30-2 SUPERIOR FIELD, TAPED VS UNTAPED” |
| N07 | complete | Presence of pain for a minimum of 3 months with documented… | unjudged: its quotation did not match the record word for word | ✓ satisfied (1.00): cites “…Documented failure over 14 months: supervised physical therapy 8 weeks (April 27,…” |
| N11 | gaps | Documented subjective patient complaints which justify… | × satisfied: cites “Complains of heavy lids” | ✓ not found (0.89): no sentence in the packet supports it |
| N11 | gaps | Documented excessive upper/ lower lid skin | × satisfied: cites “Lids appear full.” | ✓ not found (0.88): no sentence in the packet supports it |
| N11 | gaps | Signed physician’s or non-physician practitioner’s… | × satisfied: cites “Complains of heavy lids and wants surgery. Lids appear full. PLAN: Bilateral upper…” | ✓ not found (0.57): no sentence in the packet supports it |
Appendix C. One request as the engines receive it
Request B01 from the benchmark, built as complete, in full: the request record, the checklist for the governing policy, the signed visit notes and the attachment, exactly as the engines receive them (the beneficiary and clinicians are synthetic).
Request record. facet joint, initial diagnostic block; procedure 64493, diagnosis M47816, right; facility state WA; planned date of service 2026-10-19; type of bill 13X; units 1; attested by Dr. Elena Marsh, MD.
Checklist (8 items judged by the engines).
- Moderate to severe chronic neck or low back pain, predominantly axial, that causes functional deficit measured on pain or disability scale, and
- Presence of pain for a minimum of 3 months with documented failure to respond to conservative management, and
- Absence of untreated radiculopathy or neurogenic claudication (except for radiculopathy caused by facet joint synovial cyst), and
- Non-facet pathology must be ruled out based on clinical evaluation or radiology studies
- The scales used to assess the measurement of pain and/or disability must be obtained at baseline and documented in the medical record for each assessment (refer to your MAC’s LCD/LCA)
- Indicate if this request is for an initial or second diagnostic procedure
- For the first diagnostic facet joint procedure, documentation must support the criteria outlined in general documentation requirements for facet joint interventions
- Diagnostic procedures should be performed with the intent that if successful, RFA would be considered the primary treatment goal at the diagnosed level(s)
Consult note (2026-07-20, signed by Susan Feldman, MD (Pain Medicine)).
PAIN MEDICINE CONSULTATION - Harriet Lindstrom, 75yo F.
REQUEST TYPE: This request is for an INITIAL DIAGNOSTIC medial branch block. Procedure requested: CPT 64493, lumbar/sacral facet joint injection, first level, right L4-L5 and L5-S1.
CONDITION REQUIRING PROCEDURE: Moderate to severe chronic low back pain, predominantly axial, right paraspinal at L4-L5 and L5-S1, present for 7 months. Pain is worse with extension and rotation, limits standing tolerance to 15 minutes, household tasks and sleep.
FUNCTIONAL ASSESSMENT (BASELINE): Numeric Rating Scale 7/10 today. ODI 56% (severe disability). Both scales recorded today as the baseline against which post-procedure change will be measured at every follow-up.
CONSERVATIVE MANAGEMENT: Documented failure over 7 months: supervised physical therapy 8 weeks (May 11, 2026 to July 6, 2026) with core stabilization and McKenzie extension, ongoing home exercise program, meloxicam 15 mg daily for 10 weeks, acetaminophen 1 g TID, activity modification and heat. No durable relief; NRS never below 6/10.
NEUROLOGICAL EXAM: Strength 5/5 in all myotomes, reflexes 2+ and symmetric, sensation intact to light touch, straight-leg raise negative bilaterally, normal gait, no neurogenic claudication. There is no radiculopathy. Facet loading (extension with rotation) reproduces the pain right at L4-L5 and L5-S1; paraspinal tenderness over the facet lines.
IMAGING: MRI lumbar spine (July 9, 2026) demonstrates facet arthropathy with joint effusion at L4-L5 and L5-S1. No disc herniation, no central or foraminal stenosis, no fracture, no infection, no tumor. Non-facet pathology is ruled out on imaging and clinical evaluation.
INTENT: The diagnostic block is performed with the intent that, if it produces concordant relief, radiofrequency ablation will be the primary treatment at these levels.
PLAN: Proceed with lumbar/sacral facet joint injection, first level at L4-L5 and L5-S1 right under fluoroscopy. Risks, benefits and alternatives reviewed; consent obtained.
ATTESTATION: I attest that the requirements of the applicable Medicare coverage article for facet joint interventions have been met and are documented in this record. Dr. Elena Marsh, MD.Progress note (2026-09-16, signed by Susan Feldman, MD (Pain Medicine)).
PAIN MEDICINE PRE-PROCEDURE VISIT - Harriet Lindstrom, 75yo F.
INTERVAL: Seen 8 weeks after consultation. Pain unchanged: low back pain, axial, right, NRS 7/10; ODI 58% (repeat scale, same instrument as baseline).
CONSERVATIVE CARE STATUS: Home exercise continued; medications unchanged; no interval relief.
EXAM: Unchanged from consultation; neurological exam remains intact without radicular signs.
PLAN: lumbar/sacral facet joint injection, first level at L4-L5 and L5-S1 right scheduled for October 19, 2026. Anticoagulation reviewed; NPO instructions given.Attachment, pain scale log (PDF).
PAIN AND DISABILITY SCALE LOG
Patient: Harriet Lindstrom DOB 1951-03-14
Instrument: Numeric Rating Scale (0-10) and ODI (%). Same instruments at every visit.
2026-04-27 NRS 7/10 ODI 54% PT week 1
2026-05-25 NRS 7/10 ODI 54% PT week 5
2026-06-22 NRS 8/10 ODI 54% PT week 9
2026-07-20 NRS 7/10 ODI 56% baseline for procedure
Recorded by clinic staff; reviewed by Susan Feldman, MD (Pain Medicine).
Appendix D. What the engines returned for that request
Gemini. Board: P1 complete, P2 eligible, P3 in program, P4 resolved, P5 covered, P6 satisfied, P7 no gaps found; proposed decision A (affirmed); documentation step 155 s, 9 model calls, 16,355 input / 2,230 output tokens.
Jev. Board: P1 complete, P2 eligible, P3 in program, P4 resolved, P5 covered, P6 satisfied, P7 no gaps found; proposed decision A (affirmed); documentation step 9 s, 9 model calls, 30,660 input / 4,219 output tokens.
The three parts of the output follow: the router’s choice of documents per item, the evaluator’s verdict per item with the cited sentence, and the rows settled by rules without a model call. Document ids are shown by name.
D.1 Router output
Table 7. Gemini: documents routed to each item, with the router’s note.
| Item | Documents | Router note |
|---|---|---|
| Moderate to severe chronic neck or low back pain, predominantly axial, that causes functional deficit measured on pain or disability scale, and | Consult note; Progress note; Attachment, pain scale log | These sources describe the chronic axial low back pain, its severity, and the functional deficit measured by pain/disability scales. |
| Presence of pain for a minimum of 3 months with documented failure to respond to conservative management, and | Consult note; Progress note; Attachment, pain scale log | These sources document the pain duration (>3 months) and the failure of specific conservative treatments. |
| Absence of untreated radiculopathy or neurogenic claudication (except for radiculopathy caused by facet joint synovial cyst), and | Consult note; Progress note | These notes document the clinical examination findings that rule out radiculopathy and neurogenic claudication. |
| Non-facet pathology must be ruled out based on clinical evaluation or radiology studies | Consult note | This note explicitly states that non-facet pathology was ruled out by both clinical evaluation and imaging studies. |
| The scales used to assess the measurement of pain and/or disability must be obtained at baseline and documented in the medical record for each assessment (refer to your MAC’s LCD/LCA) | Consult note; Progress note; Attachment, pain scale log | These sources document the specific pain/disability scales used (NRS, ODI), the baseline values, and their consistent use. |
| Indicate if this request is for an initial or second diagnostic procedure | Consult note | This note explicitly states that the request is for an "INITIAL DIAGNOSTIC" procedure. |
| For the first diagnostic facet joint procedure, documentation must support the criteria outlined in general documentation requirements for facet joint interventions | Consult note | This note contains an attestation of compliance and also provides the detailed evidence for the general requirements. |
| Diagnostic procedures should be performed with the intent that if successful, RFA would be considered the primary treatment goal at the diagnosed level(s) | Consult note | This note explicitly states the intent to consider radiofrequency ablation (RFA) as the primary treatment if the diagnostic block is successful. |
Table 8. Jev: documents routed to each item, with the router’s note.
| Item | Documents | Router note |
|---|---|---|
| Moderate to severe chronic neck or low back pain, predominantly axial, that causes functional deficit measured on pain or disability scale, and | Consult note; Progress note; Attachment, pain scale log | jev: NOTE_1 0.92, NOTE_2 0.84, ATTACHMENT_1 0.79 |
| Presence of pain for a minimum of 3 months with documented failure to respond to conservative management, and | Consult note; Attachment, pain scale log | jev: NOTE_1 0.93, ATTACHMENT_1 0.56 |
| Absence of untreated radiculopathy or neurogenic claudication (except for radiculopathy caused by facet joint synovial cyst), and | Consult note; Progress note | jev: NOTE_1 0.90, NOTE_2 0.70 |
| Non-facet pathology must be ruled out based on clinical evaluation or radiology studies | Consult note | jev: NOTE_1 0.96 |
| The scales used to assess the measurement of pain and/or disability must be obtained at baseline and documented in the medical record for each assessment (refer to your MAC’s LCD/LCA) | Consult note; Attachment, pain scale log; Progress note | jev: NOTE_1 0.94, ATTACHMENT_1 0.83, NOTE_2 0.71 |
| Indicate if this request is for an initial or second diagnostic procedure | Consult note | jev: NOTE_1 0.96 |
| For the first diagnostic facet joint procedure, documentation must support the criteria outlined in general documentation requirements for facet joint interventions | Consult note; Progress note | jev: NOTE_1 0.89, NOTE_2 0.54 |
| Diagnostic procedures should be performed with the intent that if successful, RFA would be considered the primary treatment goal at the diagnosed level(s) | Consult note | jev: NOTE_1 0.97 |
D.2 Evaluator output
Table 9. Gemini: verdict, cited sentence and rationale per item.
| Item | Verdict | Cited sentence | Rationale |
|---|---|---|---|
| Moderate to severe chronic neck or low back pain, predominantly axial, that causes functional deficit measured on pain or disability scale, and | satisfied | Consult note: “Moderate to severe chronic low back pain, predominantly axial, right paraspinal at L4-L5 and L5-S1, present for 7 months. Pain is worse with extension and rotation, limits standing tolerance to 15 minutes, household tasks and sleep.” | The documentation describes moderate to severe, chronic (7 months), predominantly axial low back pain that causes a functional deficit. The same note quantifies this deficit using a Numeric Rating Scale (7/10) and an Oswestry Disability Index (56%), satisfying all components of the requirement. |
| Presence of pain for a minimum of 3 months with documented failure to respond to conservative management, and | unjudged | – | The evaluator could not produce a valid verdict: quote is not a verbatim substring of the cited source. |
| Absence of untreated radiculopathy or neurogenic claudication (except for radiculopathy caused by facet joint synovial cyst), and | satisfied | Consult note: “no neurogenic claudication. There is no radiculopathy.” | The neurological exam documented in the consultation note explicitly states there is no neurogenic claudication and no radiculopathy. A later progress note confirms the neurological exam remains intact without radicular signs. |
| Non-facet pathology must be ruled out based on clinical evaluation or radiology studies | satisfied | Consult note: “Non-facet pathology is ruled out on imaging and clinical evaluation.” | The clinical note explicitly states that non-facet pathology has been ruled out by both imaging and clinical evaluation, listing specific findings from an MRI and neurological exam. |
| The scales used to assess the measurement of pain and/or disability must be obtained at baseline and documented in the medical record for each assessment (refer to your MAC’s LCD/LCA) | satisfied | Consult note: “FUNCTIONAL ASSESSMENT (BASELINE): Numeric Rating Scale 7/10 today. ODI 56% (severe disability). Both scales recorded today as the baseline against which post-procedure change will be measured at every follow-up.” | The consultation note documents a baseline pain assessment using the Numeric Rating Scale (NRS 7/10) and a baseline disability assessment using the Oswestry Disability Index (ODI 56%), explicitly stating these are the baseline measures. |
| Indicate if this request is for an initial or second diagnostic procedure | satisfied | Consult note: “REQUEST TYPE: This request is for an INITIAL DIAGNOSTIC medial branch block.” | The note clearly identifies the requested procedure as an initial diagnostic block in the "REQUEST TYPE" section. |
| For the first diagnostic facet joint procedure, documentation must support the criteria outlined in general documentation requirements for facet joint interventions | satisfied | Consult note: “I attest that the requirements of the applicable Medicare coverage article for facet joint interventions have been met and are documented in this record.” | The note contains a specific attestation from the clinician confirming that the documentation meets the requirements of the applicable Medicare coverage article for these interventions. |
| Diagnostic procedures should be performed with the intent that if successful, RFA would be considered the primary treatment goal at the diagnosed level(s) | satisfied | Consult note: “The diagnostic block is performed with the intent that, if it produces concordant relief, radiofrequency ablation will be the primary treatment at these levels.” | The note explicitly states under the "INTENT" section that the purpose of the diagnostic block is to determine if the patient is a candidate for radiofrequency ablation, which would be the primary treatment if the block is successful. |
Table 10. Jev: verdict with its status probability, cited sentence with its evidence probability, per item. Jev returns no rationale; it only chooses.
| Item | Verdict (probability) | Cited sentence (probability) | Confidence |
|---|---|---|---|
| Moderate to severe chronic neck or low back pain, predominantly axial, that causes functional deficit measured on pain or disability scale, and | satisfied (1.00) | Consult note: “ODI 56% (severe disability).” (0.46) | 1.00 |
| Presence of pain for a minimum of 3 months with documented failure to respond to conservative management, and | satisfied (1.00) | Consult note: “CONSERVATIVE MANAGEMENT: Documented failure over 7 months: supervised physical therapy 8 weeks (May 11, 2026 to July 6, 2026) with core stabilization and McKenzie extension, ongoing home exercise program, meloxicam 15 mg daily for 10 weeks, acetaminophen 1 g TID, activity modification and heat.” (0.78) | 1.00 |
| Absence of untreated radiculopathy or neurogenic claudication (except for radiculopathy caused by facet joint synovial cyst), and | satisfied (1.00) | Consult note: “NEUROLOGICAL EXAM: Strength 5/5 in all myotomes, reflexes 2+ and symmetric, sensation intact to light touch, straight-leg raise negative bilaterally, normal gait, no neurogenic claudication.” (0.54) | 1.00 |
| Non-facet pathology must be ruled out based on clinical evaluation or radiology studies | satisfied (1.00) | Consult note: “Non-facet pathology is ruled out on imaging and clinical evaluation.” (1.00) | 1.00 |
| The scales used to assess the measurement of pain and/or disability must be obtained at baseline and documented in the medical record for each assessment (refer to your MAC’s LCD/LCA) | satisfied (0.94) | Consult note: “Both scales recorded today as the baseline against which post-procedure change will be measured at every follow-up.” (0.87) | 0.92 |
| Indicate if this request is for an initial or second diagnostic procedure | satisfied (1.00) | Consult note: “REQUEST TYPE: This request is for an INITIAL DIAGNOSTIC medial branch block.” (1.00) | 1.00 |
| For the first diagnostic facet joint procedure, documentation must support the criteria outlined in general documentation requirements for facet joint interventions | satisfied (0.93) | Consult note: “ATTESTATION: I attest that the requirements of the applicable Medicare coverage article for facet joint interventions have been met and are documented in this record.” (0.93) | 0.91 |
| Diagnostic procedures should be performed with the intent that if successful, RFA would be considered the primary treatment goal at the diagnosed level(s) | satisfied (0.99) | Consult note: “INTENT: The diagnostic block is performed with the intent that, if it produces concordant relief, radiofrequency ablation will be the primary treatment at these levels.” (1.00) | 0.98 |
D.3 Rows settled without a model call
These checklist rows are decided by rules on the request record and the notes’ metadata; they are identical for both engines.
Table 11. Rows settled by rules for the same request.
| Item | Status | Reason |
|---|---|---|
| the resubmission of the PAR should contain an exact match of the beneficiary’s first name, last name, date of birth to the previous submission, and the UTN associated with the previous submission | unjudged (pending extraction) | Applies only when RESUBMISSION — the inquiry does not carry a submission-sequence field, so whether this item applies cannot be determined yet. |
| Beneficiary: Beneficiary Name | satisfied | |
| Beneficiary: Beneficiary Medicare Number (also known as the MBI) | satisfied | |
| Beneficiary: Beneficiary Date of Birth | satisfied | |
| Hospital OPD: Name of facility | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Hospital OPD: PTAN/CCN | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Hospital OPD: Facility Address | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Hospital OPD: Facility National Provider Identifier (NPI) | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Physician/Practitioner: Physician/Practitioner’s Name | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Physician/Practitioner: Physician/Practitioner’s National Provider Identifier (NPI) | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Physician/Practitioner: Physician/Practitioner PTAN | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Physician/Practitioner: Physician/Practitioner’s Address | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Physician/Practitioner: Physician/Practitioner’s Fax Number | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Requester: Requester Name | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Requester: Requester Phone Number | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Requester: Requester Email Address | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Requester: Requester Fax Number | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Other: HCPCS Code(s) | satisfied | |
| Other: Diagnosis Code(s) | satisfied | |
| Other: Type of Bill | satisfied | |
| Other: Units of Service | satisfied | |
| Other: Indicate if the request is an initial or subsequent review | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
| Other: Indicate if the request is expedited and the reason why | unjudged (pending extraction) | An administrative element with no schema field to read — not captured by this engine yet, honestly pending rather than missing. |
Published on Zenodo: https://zenodo.org/records/23344517
Written by